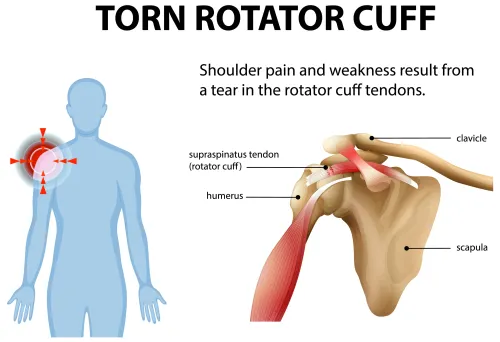
A torn shoulder labrum and an unstable shoulder can produce overlapping pain, clicking and weakness, but they do not always need the same operation. By matching your symptoms, instability pattern, imaging findings and activity demands to each option, you can have a more informed discussion about treatment.
Key takeaways
- Labral repair fixes a torn rim; stabilisation addresses repeated shoulder slipping.
- Instability history, examination findings and scans guide the treatment target.
- Rehabilitation suits selected injuries; recurrent dislocation can make surgery more relevant.
- Compare restrictions, rehabilitation length and recurrence risks before choosing surgery.
Labral repair and shoulder stabilisation are not the same operation
A labral repair reattaches a torn rim of cartilage, usually with suture anchors. A shoulder stabilisation procedure has a wider goal: preventing the upper-arm bone from repeatedly slipping, subluxing or dislocating by repairing, tightening or reconstructing several stabilising structures.
Shoulder stabilisation is an umbrella term, not one operation. The procedure may include Bankart labral repair, capsular plication or shift, remplissage for a Hill-Sachs defect, or bone-transfer surgery such as a Latarjet when glenoid bone loss makes soft-tissue repair unreliable.
| Option | Practical target | Typical role |
|---|---|---|
| Labral repair | Reattach a torn labrum and capsule | Discrete Bankart tear with little bone loss |
| Capsular stabilisation | Tighten a stretched capsule | Capsular laxity or multidirectional instability |
| Remplissage | Fill an engaging Hill-Sachs defect | Anterior instability with humeral-head bone damage |
| Latarjet or bone block | Restore the front glenoid bone and add stability | Significant bone loss or repeated dislocations |
That makes labral repair versus shoulder stabilisation a misleading either-or choice: labral repair may be one part of stabilisation. A SLAP tear near the biceps anchor can cause pain or clicking without true instability, so its MRI label does not automatically justify surgery.
The right shoulder instability treatment options depend on the direction of slipping, recurrence, sport or work demands, and the amount of glenoid and humeral-head bone loss.
Symptoms and injury patterns point to different treatment targets
Pain with clicking is a different treatment problem from a shoulder that repeatedly slips out. Shoulder labrum injury treatment cannot be selected from an MRI label alone: the injury mechanism, direction of instability, examination and bone damage must match.
| Pattern | Symptoms and cause | Likely treatment target |
|---|---|---|
| Traumatic anterior instability | A fall or contact injury causes dislocation or repeated slipping, often with apprehension when the arm is raised and rotated outward | Repair the anteroinferior labrum and capsule; add stabilisation if the shoulder remains unstable or bone loss is significant |
| Superior labral tear | Deep pain or clicking during overhead activity, without a true dislocation or slipping sensation | Assess the labrum and biceps attachment; a stabilisation procedure may not address the main complaint |
| Posterior instability | Pain or translation after a blow to the front of the shoulder, especially with the arm pushed forward or across the body | Treat the posterior labrum and capsule when they are the source |
| Multidirectional instability | Atraumatic slipping in more than one direction, often with generalised laxity | Build rotator-cuff and scapular control through structured rehabilitation; consider capsular tightening only when disabling symptoms persist |
A Bankart tear after an anterior dislocation points toward a discrete structural defect. By contrast, capsular laxity can leave no single detachable labral fragment to repair. Glenoid bone loss or an off-track Hill-Sachs lesion also changes the target, because stitches alone may not stop the humeral head from escaping.
The examination and scans decide whether a repair is enough
A positive apprehension-relocation test suggests anterior instability, but it does not decide the operation alone. The examination combines direction of translation with load-and-shift testing, sulcus sign, posterior jerk testing, capsular laxity, rotator-cuff strength and the history of recurrence. Age, collision sport, overhead work and repeated dislocations raise the failure risk of an isolated repair.
Findings that change the surgical choice include:
- Plain AP, axillary and specialised glenoid-view radiographs show dislocation, a bony Bankart fragment or a large Hill-Sachs defect.
- MRI arthrography identifies a Bankart, SLAP or posterior labral tear, but an abnormal labrum can be incidental in throwing athletes and does not prove that repair will relieve pain.
- CT with three-dimensional reconstruction measures glenoid bone loss accurately. Substantial deficiency makes soft-tissue repair less reliable.
- The glenoid-track assessment shows whether a Hill-Sachs defect is on-track or engaging. An off-track lesion can require remplissage or a bone procedure.
Labral repair versus shoulder stabilisation therefore depends on the structure causing instability, not the scan label alone. This is the practical framework for shoulder labrum injury treatment:
| Option | What it addresses | When it fits |
|---|---|---|
| Isolated labral repair | Re-attaches a torn labrum with anchors | Traumatic instability with minimal glenoid bone loss and no engaging Hill-Sachs defect |
| Broader stabilisation | Adds capsular tightening, plication or remplissage | Capsular laxity, recurrent translation or an engaging humeral-head defect |
| Bone procedure, such as Latarjet | Restores glenoid support and adds a sling effect | Meaningful glenoid bone loss, repeated dislocations or failed soft-tissue repair |
When rehabilitation is reasonable and when surgery becomes more relevant
A first instability episode without a major fracture or persistent mechanical problem usually justifies activity modification and structured physiotherapy before surgery. The programme targets rotator-cuff strength, scapular control and movement confidence.
| Situation | Reasonable first step | When surgery becomes more relevant |
|---|---|---|
| First dislocation or subluxation | Sling or pain relief as advised, followed by progressive physiotherapy | Continued slipping, a trapped fragment or a symptomatic labral tear |
| Multidirectional laxity | Prolonged rehabilitation focused on strength and control | Disabling instability despite consistent supervised treatment |
| Recurrent instability | Protect the shoulder and reassess the injury pattern | Repeated dislocations, contact-sport demands or failed rehabilitation |
| Bone or combined soft-tissue damage | Activity changes while scans clarify the risk | Glenoid bone loss, an off-track Hill-Sachs lesion or a repair unlikely to hold |
A labral repair suits a repairable tear; broader shoulder stabilisation becomes more useful when stretched capsule, recurrent translation or bone loss also drives the instability. The operation could involve capsular tightening, remplissage or a bone-block procedure rather than labral repair alone.
Searching “labral repair or shoulder stabilisation Mumbai” identifies a location, not the correct treatment. Ask how much bone loss exists, whether the lesion is on-track or off-track, and what recurrence risk follows each option. Surgery also requires staged rehabilitation; return to contact sport or heavy overhead work often takes about five to six months.
Compare the recovery trade-offs before choosing a procedure
Compare recurrence risk against the motion and time you need for work or sport: the operation with the lowest instability risk is not automatically the best choice if it creates unnecessary stiffness or a longer recovery.
| Option | Recurrence trade-off | Motion, work and sport |
|---|---|---|
| Nonoperative care | Avoids surgical complications, but recurrent instability can continue, especially after repeated dislocations or with bone loss. | Motion is preserved initially; strengthening and activity changes may suit low-demand work, but contact sport and risky overhead activity may remain restricted. |
| Labral repair | Best for a repairable traumatic tear without major bone loss; recurrence rises in young collision athletes, repeated dislocators and off-track Hill-Sachs lesions. | Usually preserves useful motion; sling protection and staged rehabilitation delay heavy work and contact sport, often for about 5–6 months. |
| Broader stabilisation | Capsular shift, remplissage or combined repair addresses laxity or associated defects that a labral repair alone misses. | More protected rehabilitation can mean more stiffness, but returning too early increases reinjury risk. |
| Bone-block surgery | A Latarjet or similar procedure suits meaningful glenoid bone loss and can reduce recurrence when soft-tissue repair is insufficient. | It is more invasive, with graft, nerve, stiffness and arthritis risks; strength and contact-sport recovery require careful progression. |
Ask which procedure matches your glenoid and humeral-head bone loss, whether the lesion is on-track or off-track, and the surgeon’s expected recurrence rate. Dr Dhirav Shah- Orthopaedic Surgeon 8104619499 should also explain the rehabilitation restrictions for your actual job and sport, not just the operation name.
A search for labral repair or shoulder stabilisation Mumbai, or shoulder arthroscopy surgeon Vile Parle, identifies a location—not a diagnosis. Compare the proposed procedure and rehabilitation plan.
Related service
Labral Repair Treatment Labral tears occur in the labrum -the cup-shaped fibrocartilage attached to the ball and socket joint of the shoulder. View service → |
Frequently asked questions
What is the difference between labral repair and shoulder stabilisation?
Labral repair reattaches a torn shoulder labrum, usually with suture anchors. Shoulder stabilisation aims to stop repeated subluxation or dislocation by repairing, tightening or reconstructing stabilising structures.
How do doctors decide which shoulder instability treatment is appropriate?
They assess your symptoms, injury history, shoulder movement and stability, then review scans for labral tears, bone loss and other structural damage.
When is rehabilitation reasonable instead of surgery?
Rehabilitation is reasonable when the shoulder is not repeatedly slipping and the injury pattern can improve with supervised strengthening, movement retraining and activity changes.
What recovery trade-offs should you compare before shoulder surgery?
Compare immobilisation, time away from work or sport, physiotherapy demands, movement restrictions, recurrence risk and the procedure needed for your specific injury.
Keywords